Medically reviewed by Lynn Williams, PA-C · Reviewed September 1, 2026
The most damaging belief about psoriasis has very little to do with the skin. It is the assumption that raised, scaly patches are a sign of poor hygiene — or, worse, something a person might pass along in a handshake, a locker room, or a swimming pool. Neither is true. Psoriasis is not contagious, and you cannot catch it from someone the way you can catch chickenpox or a cold.
What psoriasis actually is turns out to be far more useful to understand. It explains why certain treatments work, and why flares seem to come out of nowhere. It also explains why the plan that helps one person may not be the right plan for the next. Here is what patients most often want to know: the main types, what sets a flare off, how psoriasis differs from eczema, and how dermatologists decide on treatment.
What Psoriasis Is — and What It Isn't
Psoriasis is a problem of pace. Normally, skin cells are made deep in the skin and take weeks to travel to the surface. In psoriasis, the body makes new skin cells in days rather than weeks. Those cells pile up faster than the skin can shed them, and the result is the thickened, scaly patch you can see and feel.
The reason behind that speed is immune, not cosmetic. Something goes wrong in the immune system, so T-cells that normally fight infection attack the body's own skin cells instead. Genetics play a part too — having a parent, grandparent, brother, or sister with psoriasis raises your risk of developing it.
Two things follow from that. First, nothing you did or failed to wash caused this. Second, psoriasis is driven by the immune system, not only by the skin surface. So your dermatologist will ask about more than the patches themselves — including how you are feeling elsewhere in your body, such as in your joints. Psoriasis is a long-term condition that tends to come and go, and the goal of treatment is steady control rather than a one-time fix.
The Main Types of Psoriasis
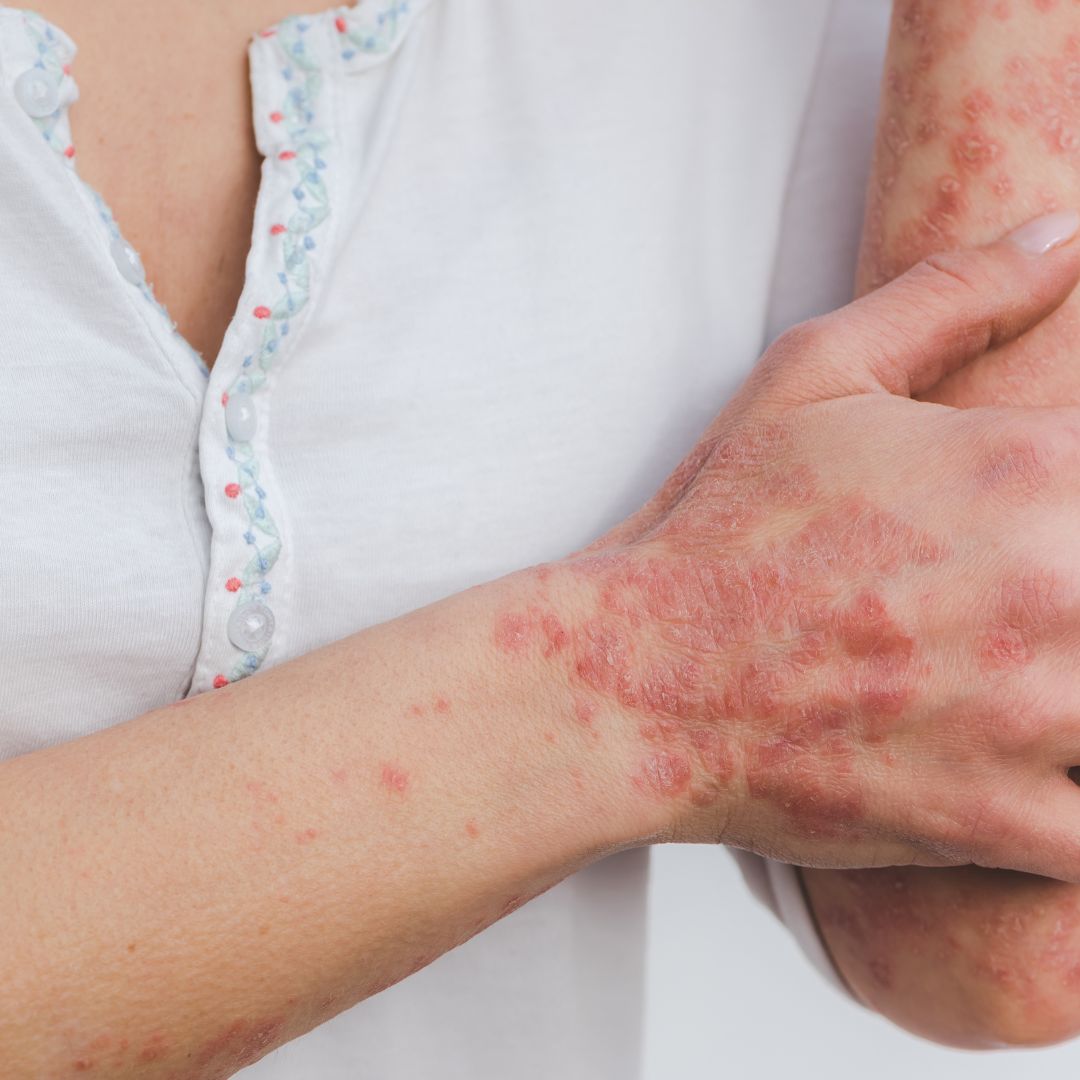
The pattern matters, because it shapes what treatment makes sense. One type accounts for the large majority of cases: about 80% to 90% of people with psoriasis get plaques — raised patches coated with a silvery-white scale. That is plaque psoriasis, and it is the picture most people have in mind when they hear the word.
Where those plaques land is fairly predictable. Plaques can appear anywhere on the skin, but they are most likely on the knees, elbows, lower back, and scalp. That last one catches people out — flaking that has been written off as stubborn dandruff for years is sometimes scalp psoriasis.
Not every presentation looks like a classic plaque, which is why an in-person exam matters:
- Small, drop-shaped spots that come on after an illness. Infection, such as strep throat, is a recognized trigger, so a flare can follow closely on the heels of a sore throat.
- Patches in skin folds — under the breasts, in the armpits, in the groin — where friction and moisture change how the skin looks and there is far less visible scale.
- Involvement of areas that are easy to overlook or to misread: the scalp, the nails, and the face.
Because psoriasis can appear anywhere on the skin, a dermatologist will usually look beyond the patch that brought you in. What is happening on your nails or in a skin fold can change the diagnosis and the plan.
Psoriasis vs. Eczema: How to Tell the Difference
This is the most common mix-up we see, and it is an understandable one — both can leave you with red, irritated, itchy skin. There are patterns that help a clinician separate them, though none of them is a reliable do-it-yourself test.
Location is the first clue. Psoriasis has favorite sites: the knees, elbows, lower back, and scalp — often the outside of a joint. Eczema more typically settles in the bend of the elbow or behind the knee, and in children it frequently involves the face.
The surface of the patch is the second clue. In psoriasis you will often see raised patches coated with a silvery-white scale, with a border that tends to be well defined. As a general distinction, dermatologists describe eczema as looking redder and more weepy, with a thinner scale and edges that blur into the surrounding skin. Itch is part of the conversation too. Your dermatologist will ask how intense it is, when it is worst, and whether scratching changes how the skin looks. The answers point in different directions.
If you have already looked into how to tell eczema from rosacea, you know how much overlap there is between common facial and body rashes. Getting the label right is not academic: the plan for psoriasis and the dermatologist-approved options for eczema are not the same, and treating one as though it were the other tends to waste months.
What Triggers a Flare
Psoriasis often has a rhythm — quiet stretches broken by flares. Knowing your own triggers will not make the condition disappear, but it makes flares less mysterious and easier to head off.
The best-documented triggers are ordinary life events. Stress, skin injuries, and infections — a cut, a bad sunburn, or strep throat — can all set psoriasis off. That is worth remembering before a beach weekend, and worth mentioning to your dermatologist if a flare followed a rough few weeks at work or a round of illness in the house.
Medication is another recognized trigger. Some medications, including lithium, prednisone, and hydroxychloroquine, can provoke psoriasis or make it worse. This is information to bring to an appointment, not to act on alone — never stop a prescribed medicine on your own. Bring a full list of what you take to your visit so the conversation can happen with the clinician who prescribed it.
Environment and habits round out the list. Weather, especially cold, dry weather, along with tobacco and heavy drinking, are all recognized triggers. Main Line winters are exactly the conditions patients tell us make their skin worse, and a dry, over-heated house does not help.
How Psoriasis Is Treated
There is no single psoriasis treatment, and that is a good thing — it means there is room to match the plan to the person. There are several options: creams you put on the skin, light therapy, medicines that work throughout the body, and biologic drugs that target specific immune pathways. Think of it as a ladder.
The bottom rung is topical: creams and ointments applied directly to the skin, which is where most people with limited, localized disease start. Used consistently, and in a form that suits the body part being treated, these do a great deal of work. A scalp needs a different formulation than an elbow, and skin folds and the face need gentler options still.
The next rung is light therapy, delivered in a controlled clinical setting rather than at a tanning salon. It is an established option for moderate to severe plaque and guttate psoriasis. Today, narrowband UVB is the form used most often, because it has fewer side effects compared with broadband UVB or PUVA.
Above that sit medicines that work throughout the body, including biologics aimed at specific parts of the immune response. These are considered for more extensive or stubborn disease. Choosing among them is a clinical decision, one that weighs how severe the disease is, which body sites are involved, how much the condition is affecting daily life, and what other health conditions and medications are in the picture. That is the conversation to have when you see a dermatologist about your psoriasis, and it is a conversation that gets revisited as your skin changes.
When to See a Dermatologist
Plenty of people manage mild, occasional dryness with a good moisturizer and never need more. Psoriasis is different, and there are clear signals that over-the-counter management has run out of road:
- Patches that keep coming back in the same place, or that are spreading rather than settling.
- Thick, silvery scale that does not respond to drugstore products after a few weeks of consistent use.
- Involvement of the scalp, face, nails, or skin folds — areas where the wrong product can do harm and the right one is a prescription decision.
- Itch, discomfort, or visible patches that are affecting your sleep, your clothing choices, or how you feel about being seen.
- Any doubt about the diagnosis. If you are not certain whether you are treating psoriasis or something else, an exam settles it quickly.
One symptom deserves particular attention: joint pain. Because psoriasis is driven by the immune system rather than by the skin surface alone, symptoms elsewhere in the body matter. If you have psoriasis and you are also noticing joint pain, stiffness that is worst in the morning, or swelling in the fingers or toes, say so at your appointment. Do not wait for your next routine visit to raise it.
Frequently Asked Questions
Is psoriasis contagious?
No. Unlike chickenpox or a cold, you cannot catch psoriasis from someone. It is an immune-mediated condition, not an infection, and nothing about it reflects hygiene. Sharing a towel, a pool, or a handshake carries no risk.
What is the difference between psoriasis and eczema?
Broadly: the location, the border, and the surface. Psoriasis tends to produce raised patches coated with a silvery-white scale, most often on the knees, elbows, lower back, and scalp. Eczema is generally described as redder and weepier, with softer edges, and it often favors the creases of the elbows and knees. The two can look similar enough that an exam is the sensible way to settle it.
Can psoriasis appear on your face?
Yes. Plaques can appear anywhere on the skin, though they are most likely on the knees, elbows, lower back, and scalp. Facial skin is thinner and more reactive than skin on an elbow, so treatment there is chosen carefully — it is not a place to experiment with strong over-the-counter products.
Does psoriasis go away on its own?
Patches can quieten down and then return, which is why psoriasis is described as a long-term condition rather than a passing rash. Flares often follow a trigger — stress, a skin injury, or an infection such as a cut, a bad sunburn, or strep throat are all recognized ones. With the right plan, most people get their skin to a calm, comfortable baseline and keep it there.
Get Your Psoriasis Properly Evaluated
Psoriasis is manageable, and the right treatment depends on your type, severity, and history. Bryn Mawr Dermatology's board-certified dermatologists see patients by appointment in Villanova, Collegeville, and Wayne/Chesterbrook. Book an appointment to be evaluated.
This article is for general educational purposes and is not a substitute for individual medical advice, diagnosis, or treatment. Do not start, stop, or change any medication based on what you read here. Talk with a qualified healthcare provider about your own skin and health history.
Editor's note: this article consolidates Bryn Mawr Dermatology's earlier psoriasis posts into a single resource.